

A Singapore study of 2,987 patients suggests that assessing breast cancer recurrence risk requires a closer look at the tumour, even when lymph nodes are clear.
“The cancer has not spread to your lymph nodes.”
For someone diagnosed with breast cancer, those words can bring enormous relief. Amid conversations about surgery, treatment and an uncertain future, they offer something encouraging to hold on to.
But how much can that finding tell you about the years ahead?
A Singapore study suggests that some patients whose breast cancer has not reached the lymph nodes can still face a meaningful risk of recurrence. Their outcomes may resemble those of patients with cancer in a small number of lymph nodes.
The finding adds local evidence to an important conversation: clear lymph nodes are encouraging, but they do not tell the whole story about whether breast cancer might return.
What Does “Node-Negative” Breast Cancer Mean?
Lymph nodes are small structures that form part of the immune system. In breast cancer, doctors assess nearby nodes, including those in the armpit, to help understand how far the disease has spread.
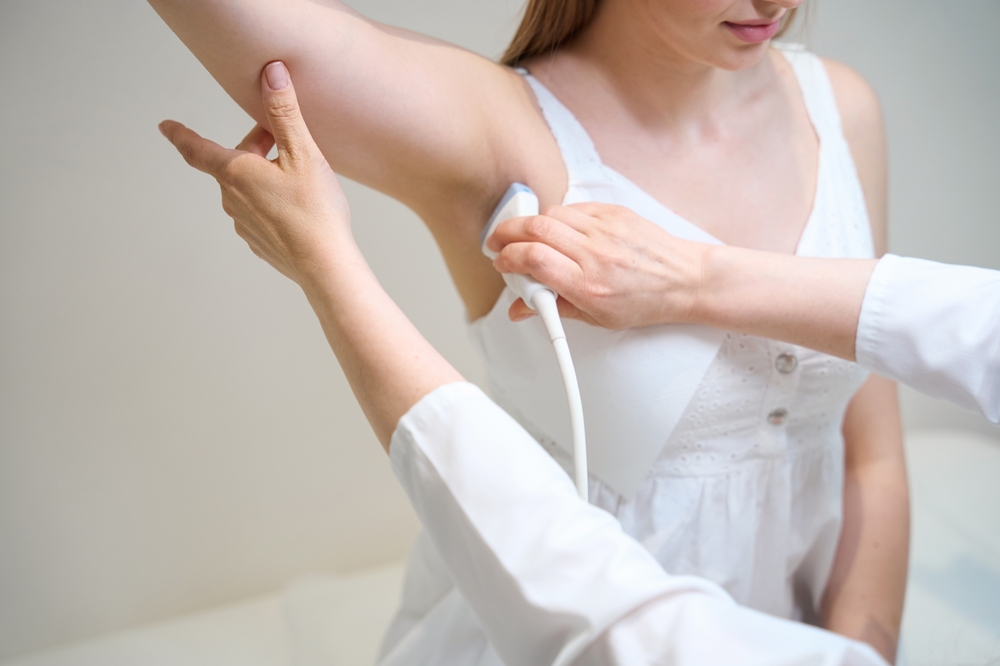
“Node-negative” means no cancer was found in the lymph nodes assessed, while “node-positive” means cancer was detected.
However, treatment decisions also depend on other factors such as the tumour’s size and biological features. Two patients can therefore both have node-negative breast cancer yet receive different advice about treatment after surgery.
What Makes Breast Cancer “Higher Risk”?
“Higher risk” describes a greater likelihood of breast cancer returning after treatment, not that recurrence is inevitable.
Doctors assess this risk using several pieces of information. These include the size of the tumour, whether lymph nodes are involved and how many are affected, and the tumour’s grade ie. how abnormal its cells look under a microscope.
They also consider biological features, such as hormone receptors and markers of how actively the cancer cells are dividing. In some cases, tests that examine the activity of genes in the tumour can help refine the assessment.
A larger tumour or a tumour with more aggressive features may therefore raise concern even when no cancer is found in the lymph nodes. Equally, two patients with lymph-node involvement may have different levels of risk because their cancers differ in other ways.
What Did The Study Find?
The RACES study examined records from 2,987 patients in Singapore’s Joint Breast Cancer Registry who were diagnosed between 2010 and 2017. Researchers followed their outcomes for a median of more than eight years.
All had hormone receptor-positive, HER2-negative (HR+/HER2−) early breast cancer. In this subtype, hormones can help fuel cancer growth, while the cancer is not classified as HER2-positive based on testing for the HER2 growth-related protein. These features help doctors choose treatment.
According to the study announcement, the seven-year outcomes differed substantially within the node-negative group:
| Patient Group | Reported Rate Of Recurrence Or Death Within Seven Years |
|---|---|
| Lower-risk patients without lymph-node spread | 9.4% |
| Higher-risk patients without lymph-node spread | 16.7% |
| Patients with cancer in one to three lymph nodes | 16.4% |
The higher-risk, node-negative group had tumour or disease characteristics associated with a greater likelihood of recurrence, despite having no lymph-node involvement. The similar figures in the latter two groups illustrate why lymph-node status alone can leave important questions unanswered.
*These patients were diagnosed between 2010 and 2017, before adjuvant CDK4/6 inhibitors were introduced, so their outcomes may not fully reflect those of patients receiving treatment today.
What Could Explain This?
The RACES study highlighted Ki67, a marker measured in tumour tissue that gives an indication of how actively cancer cells are dividing.
A higher Ki67 result generally points towards more rapidly dividing cells. However, testing and scoring methods matter, and the result needs to be interpreted alongside other tumour features.
Dr Elaine Lim, the study’s principal investigator and a Senior Consultant in the Division of Medical Oncology at the National Cancer Centre Singapore (NCCS), emphasised the importance of these conversations:
“RACES’ findings reinforce the need to look beyond lymph-node involvement when assessing recurrence risk, so that clinicians have early conversations with patients about their individual risk and discuss available treatment options to enable them to make informed care decisions,” she said.
Why Might Treatment Continue After Surgery?
Removing the tumour is a major step. Treatment after surgery, known as adjuvant treatment, aims to reduce the chance of cancer returning.
For hormone receptor-positive breast cancer, this often includes endocrine therapy, which blocks hormone production or interferes with hormones acting on cancer cells. It may be prescribed for several years. Other treatments depend on the patient’s cancer characteristics and circumstances.
Being offered further treatment after surgery is often part of a plan to lower future risk by killing cancer cells that may remain or slowing or stopping their growth.
What Should Patients Ask About Their Own Risk?
A useful starting question is: “Beyond my lymph nodes, which features of my cancer affect the chance of it returning?”
Ask your doctor to explain your tumour size, grade and biomarker results, and how these affect the recommended treatment. If further testing is suggested, ask whether the result could change the plan.
It can also help to ask how much each treatment is expected to reduce your individual risk, what side effects to expect, and what support is available if treatment becomes difficult.
RACES was conducted through a collaboration between NCCS and Novartis Singapore, with NCCS as regulatory sponsor and funding from Novartis.
External References
- Ma J, Rozali E, Chu SM, Lee FM, Low YF, Lim EH. Risk of recurrence in HR+/HER2− early breast cancer in pre-adjuvant CDK4/6 inhibitor era: Data from Singapore. ePoster 647eP presented at: ESMO Congress 2026; 23–27 October 2026; Madrid, Spain.

