
Research into GLP-1 drugs and colorectal cancer risk is sending mixed messages. Here is what the findings mean for patients weighing treatment benefits against an uncertain long-term picture.
A medicine helps people lose weight and control diabetes. Since obesity and diabetes are linked to colorectal cancer, it seems reasonable to expect the medicine to lower that risk too.


Yet research into GLP-1 receptor agonists is producing a less straightforward picture. Some findings suggest protection, others raise concerns, and some show no meaningful difference.
For patients, this creates an uncomfortable question: could a treatment that improves metabolic health carry an unexpected bowel cancer risk?
Current evidence does not establish that GLP-1 drugs cause colorectal cancer. It does, however, leave questions that deserve careful investigation, particularly as treatment becomes more widespread and prolonged.
What Prompted the Bowel Cancer Concern?
In a meta-analysis by Ying Zhong and colleagues, seven retrospective cohort studies involving over five million people were combined and analysed. The 2025 paper in BMC Gastroenterology reported a pooled relative risk of 2.31. suggesting an association with more than twice the colorectal cancer risk in that analysis. (This does not establish that the medicines caused the increase)
However, a separate analysis within the same paper found no statistically significant association with colorectal cancer incidence. Its estimate was highly uncertain, and results varied substantially between studies.
These findings cannot be translated into a reliable number of extra cancers caused by treatment. They also illustrate why a large headline sample does not automatically settle a medical question.
Retrospective studies examine existing records. Differences in patients’ health, treatment choices and access to investigations can influence results. Combining those records does not remove these limitations.
What Have Other Studies Found?
A 2026 US study compared people starting GLP-1 medicines with those starting DPP-4 inhibitors, another diabetes treatment. Researchers matched 86,083 pairs using patient characteristics to make the groups more comparable.
They found no statistically significant difference in colorectal cancer incidence. However, colonic polyps were recorded in 5.9% of GLP-1 users, compared with 5.3% of DPP-4 inhibitor users.
That is an absolute difference of 0.6 percentage points, or approximately six additional people with recorded polyps per 1,000 patients over the study period.
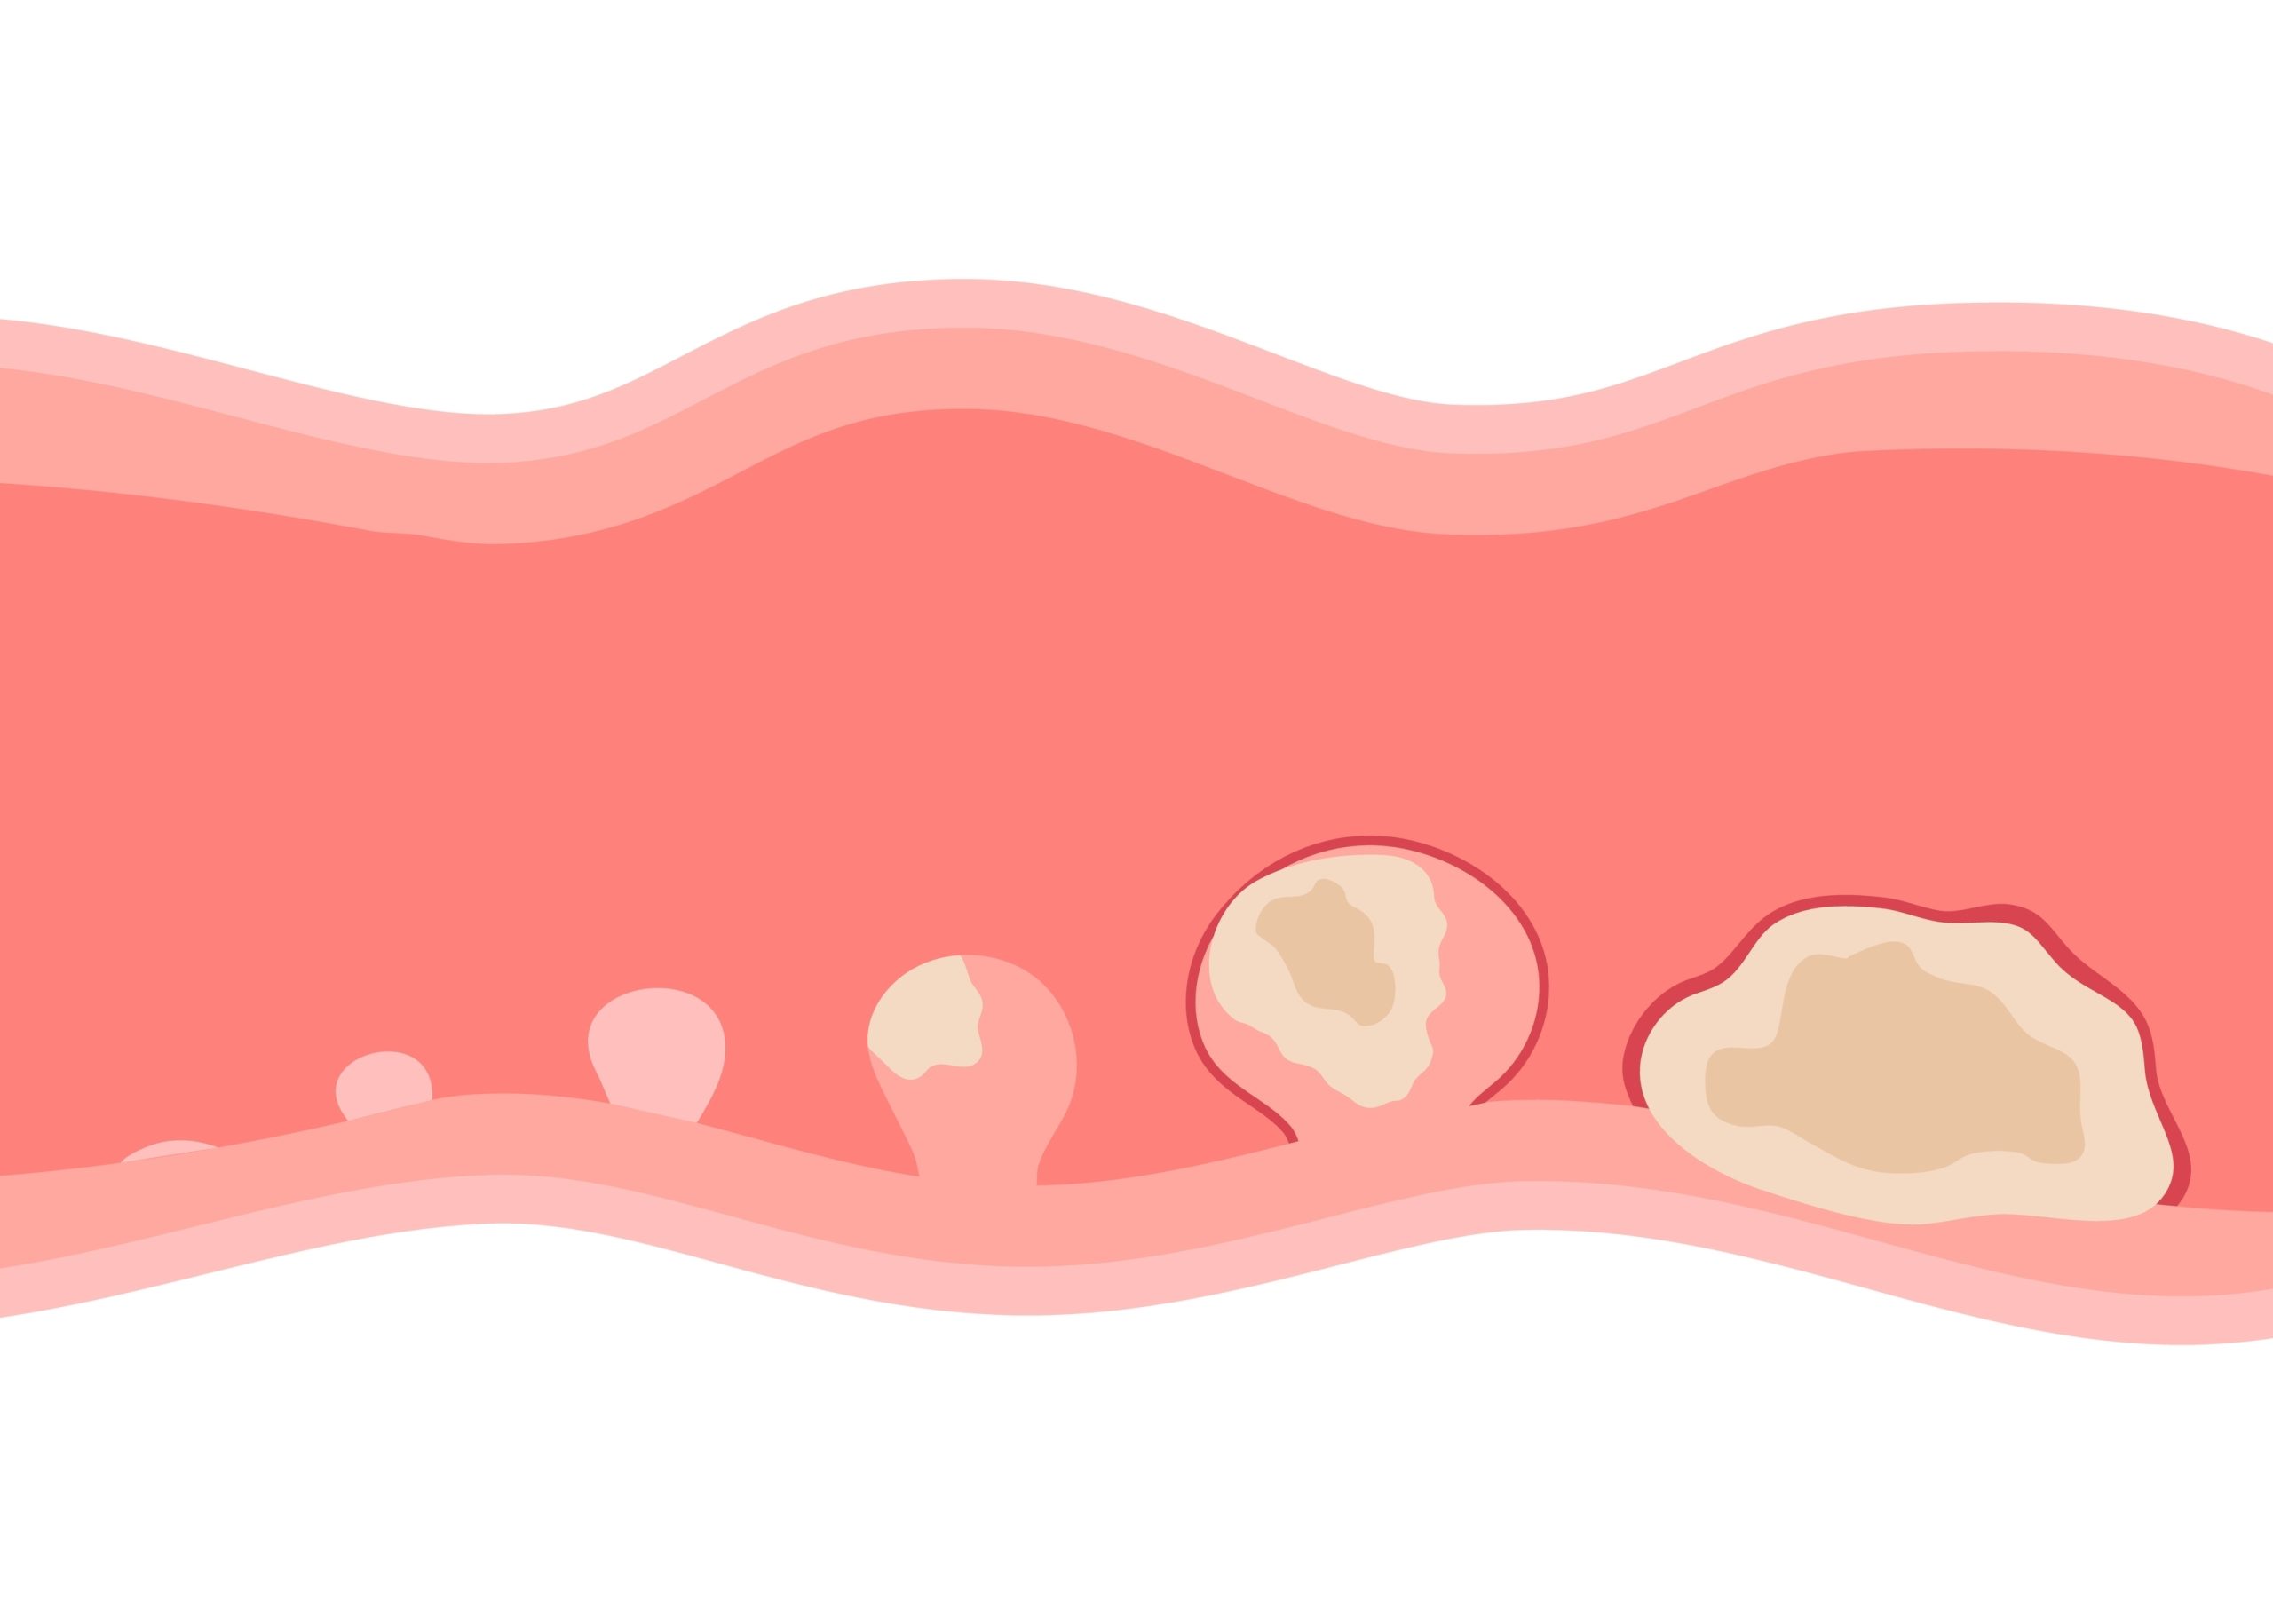
Polyps are not the same as cancer. Polyps are growths in the bowel lining. Some types can become cancerous over time, but finding more polyps does not prove that a medicine causes more cancers.
Meanwhile, a network meta-analysis of 68 randomised trials, involving 207,200 participants, identified a colorectal tumour signal with injectable semaglutide at 2.4 mg weekly. Other studied GLP-1 medicines did not show a statistically significant association.
The authors described this as a potential signal requiring validation. Its “colorectal tumour” outcome should not be treated as interchangeable with confirmed colorectal cancer.
Nor should a semaglutide finding automatically be extended to tirzepatide, a different medicine that activates both GIP and GLP-1 receptors. Its potential effects on cancer risk require separate assessment.
Why The Difference in Evidence?
There are plausible biological explanations on both sides.
Reducing excess body fat and improving insulin resistance could influence processes associated with cancer, including chronic inflammation. Researchers have also proposed that GLP-1 signalling might affect intestinal cell growth and the gut microbiome. These are possible biological explanations, not proof that treatment either prevents or promotes cancer.
Study design complicates the picture further. Someone prescribed one diabetes medicine may have more advanced disease, a different body weight or other health conditions than someone prescribed another.
A 2026 review in Nature Reviews Clinical Oncology highlights prescribing and detection biases in observational research. Furthermore, randomised trials may follow patients for too little time, or record too few cancers, to provide firm answers.
What Would Better Research Mean?
Stronger research would follow people from the start of treatment, recording their medicine, dose, screening history and other cancer risk factors. Researchers would also need to distinguish cancers already developing before treatment from those diagnosed much later.
They would also account for smoking, obesity, diabetes severity, previous polyps and family history, while checking whether cancers developed long enough after treatment started to plausibly relate to exposure.
These are priorities for stronger research, not assurances that prospective studies can eliminate every source of bias. Longer follow-up and consistent cancer definitions remain essential. Of course, all these are also dependent on the circumstances of the trial, patients and funding.
What Should Patients Do?
Treatment is ultimately a balancing act between risk and benefit – and the benefits of GLP-1 should not be scoffed at.
In the SELECT randomised trial, researchers studied people with existing cardiovascular disease and overweight or obesity, but without diabetes.
Over an average of about 40 months, a heart attack, stroke or death from cardiovascular causes occurred in 6.5% of those receiving semaglutide 2.4 mg, compared with 8.0% receiving a placebo.
In other words, around 65 in every 1,000 people receiving semaglutide experienced one of these events, compared with 80 in every 1,000 receiving placebo.
For someone at substantial risk of heart disease complications, that benefit matters. Someone with little medical need for weight-loss treatment faces a different balance! The decision therefore depends on what the medicine is expected to achieve for the individual, alongside its known side effects and remaining uncertainties.
Start with a conversation about your own health, rather than assuming a study headline applies directly to you.
Tell your prescribing doctor about a family history of bowel cancer, previous advanced polyps or an inherited condition that increases cancer risk. These affect your underlying risk, although researchers have not established precisely how they interact with GLP-1 treatment.
Keep bowel cancer screening up to date. In Singapore, Healthier SG Screening offers a faecal immunochemical test, or FIT, to eligible Singaporeans aged 50 and above. People at higher risk may need earlier assessment or a different screening plan.
The evidence leaves room for caution, but it does not justify a conclusion that these medicines cause bowel cancer. A thorough discussion with your doctor should cover three things: the benefit you can expect, your personal cancer risk and whether your screening is on track.

